
IISPPR

Category: Health

Health
Kaustubh Lipare

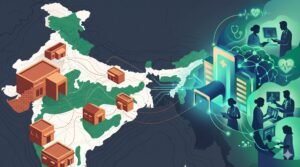
District-Level Healthcare Infrastructure and Outcome Gaps in India: An Empirical Analysis of Secondary Care Specialist Shortfalls and Primary Infrastructure

Authors:  ¹Kaustubh R. Lipare, ²Najuka Jadhav, ³Kaavya Parashar, ⁴Enugandula Gangasairam, ⁵Indu Bharti, ⁶Daksh Pokar ABSTRACT Substantial public financial investments under the National Health Mission (NHM) have expanded physical health infrastructure across India. However, distinct district-level disparities in maternal and child health outcomes persist. This study evaluates whether variations in the Infant Mortality Rate (IMR) are driven primarily by deficits in physical infrastructure (‘bricks’) or critical structural shortages of clinical specialists (‘brains’) at referral centers. Utilizing a quantitative, cross-sectional, and ecological design, we analyzed a stratified systematic sample of 80 administrative districts from two Empowered Action Group (EAG) states (Uttar Pradesh and Chhattisgarh) and two Non-EAG states (Maharashtra and Tamil Nadu). Multivariate Ordinary Least Squares (OLS) regression models evaluated the predictive impact of primary clinic density, public hospital bed density, specialist doctor vacancy rates, and private sector delivery shares on district IMR, while controlling for female literacy and multidimensional poverty. Physical primary clinic density is relatively uniform across study regions and approaches standard Indian Public Health Standards (IPHS). Conversely, acute specialist physician vacancies at Community Health Centres (CHCs) average 79.1% in EAG districts compared to 36.5% in Non-EAG cohorts. Multivariate regression models reveal that the specialist doctor vacancy rate is the single most powerful statistical predictor of elevated district IMR (p < 0.001), carrying 5.2 times greater relative explanatory weight than primary clinic footprint (|β*| = 0.692 vs. |β*| = 0.133). Furthermore, a distinct moderation tipping point is observed: the marginal statistical return of constructing additional primary facilities flattens to zero once local specialist vacancies cross the 75% to 85% threshold. Diminishing returns exist for capital expenditure dedicated to building additional physical health structures if they remain unstaffed clinical shells. Policy instruments must prioritize human resource retention packages, functional secondary care, and verified institutional service readiness to accelerate progress toward regional Sustainable Development Goal (SDG) health targets. Keywords: Infant Mortality Rate; Healthcare Infrastructure; Specialist Vacancies; Indian Public Health Standards; Ecological Study; Public Policy 1. INTRODUCTION 1.1 Background and Problem: Spatial Heterogeneity in Health Outcomes While India has achieved significant macroeconomic progress, state-level maternal and child health averages conceal a sharper reality on the ground: the physical presence of a health facility on a government register does not mean that facility is functionally equipped to handle an obstetric or neonatal emergency. Historically, public health policy in India has prioritized the expansion of the built environment—focusing heavily on expanding the sheer volume of Sub-Centres, Primary Health Centres (PHCs), and hospital beds (Ministry of Health and Family Welfare [MoHFW], 2022). This persistent capital focus has treated district-level shortfalls primarily as a physical resource supply problem. What remains far less settled is whether the more consequential bottleneck lies in the institutional readiness and clinical capacity of these existing structures. Specifically, it remains unclear whether peripheral and secondary facilities are staffed by the medical specialists required to manage complicated deliveries, and whether a functioning referral pathway exists to transfer a patient safely from a primary outpost to a center equipped to provide emergency neonatal and obstetric care. This operational tension between physical asset expansion (‘bricks’) and clinical human resource availability (‘brains’) forms the core operational puzzle of contemporary Indian healthcare delivery (Patel & Ladusingh, 2015). Therefore, a critical empirical question arises: do localized bottlenecks in clinical specialist availability and secondary-tier referral capacity function as the primary drivers of district-level infant mortality, rather than an absolute deficit in primary outpatient structures? 1.2 Magnitude of District-Level Disparity The scale of this underlying disparity is considerable and spatially clustered across India’s administrative geography (Goli et al., 2022). Approximately 448 of India’s 640 districts report a maternal mortality ratio above the threshold set by the Sustainable Development Goals (SDG-3), with the most vulnerable zones concentrated across the central, eastern, and north-eastern regions (Goli et al., 2022). Infant mortality follows a similarly uneven spatial pattern, with high-mortality hotspots remaining deeply entrenched across central India and northern Uttar Pradesh even after adjusting for socioeconomic confounders and spatial autocorrelation (Puranik et al., 2018; Ranjan & Dwivedi, 2022). Within the 80-district sample analyzed in this study, the Infant Mortality Rate (IMR) ranges from 9.20 to 68.10 deaths per 1,000 live births—a seven-fold spread—while specialist doctor vacancy at Community Health Centres (CHCs) spans from 15.20% to 89.40%. Crucially, districts in Empowered Action Group (EAG) states report an average IMR that is two and a half times higher than that of non-EAG states (48.60 vs. 19.48 deaths per 1,000 live births), alongside a specialist vacancy rate that is more than double (79.06% vs. 36.51%). This comparative cohort framework is methodologically and substantively significant: it evaluates two functionally distinct health systems operating under the exact same national policy guidelines. Investigating this regional divide allows us to determine whether these systemic outcome gaps are primarily a function of physical infrastructure layout or if they are driven by severe, localized specialist shortfalls and secondary referral voids. 1.3 Rationale and Policy Relevance The stakes of resolving this structural puzzle are high because national capital expenditure tracks whichever explanation policymakers accept. Flagship national programmes, most notably the National Health Mission (NHM) and the Pradhan Mantri Ayushman Bharat Health Infrastructure Mission (PM-ABHIM), direct substantial public funding toward physical facility construction on the implicit premise that expanding the built environment is the primary lever for closing regional outcome gaps (MoHFW, 2022). If, however, the binding constraint in India’s worst-performing districts is not the number of physical buildings but rather the availability of specialized clinical staffing and secondary referral capacity, continued capital investment in construction will fail to move mortality figures in high-burden districts, leading to a severe misallocation of scarce public resources. This study directly tests the hypothesis that physical primary structures yield diminishing returns on infant survival when they are decoupled from functional secondary-care specialists, providing a necessary empirical baseline to guide national health infrastructure allocation. 1.4 The Research Gap The existing literature fails to resolve this tension due to fragmented study designs. Public health research tends to examine either socioeconomic determinants—such as rural-urban coverage gaps and maternal literacy (Panda et

Read More »
Health
Divya Vashisht

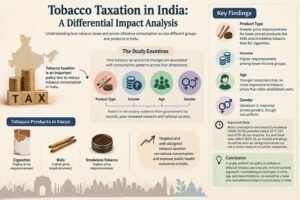
Tobacco Taxation in India: A Differential Impact Analysis

This study examines how tobacco taxes and price changes are associated with consumption across product type, income, age, and gender in India. Evidence suggests varying price responsiveness, while historical data limitations highlight the need for cautious interpretation of current tax effects.

Read More »
Health
Rajat Rao

Impact of Social Isolation on Elderly People

Social isolation in elderly individuals, particularly women aged 60-69, is linked to health issues such as depression, cardiovascular disease, and dementia. Factors like hearing loss, loss of a spouse, and low social engagement contribute to isolation. The COVID-19 pandemic worsened loneliness due to financial concerns and lack of digital connectivity. Those with lower education levels or divorced individuals are especially vulnerable. Research highlights that social connectedness improves well-being and longevity. Initiatives like community outreach, telehealth services, and digital literacy programs can help mitigate the impact of isolation, fostering stronger social ties and enhancing quality of life for older adults.

Read More »
Health
Palak Kuraichya

Portrait of a serial killer

The “Portrait of a Serial Killer” takes you inside the twisted minds of those who kill repeatedly. It uncovers how childhood trauma, emotional neglect, antisocial personality disorder and other deep psychological disorders shape their need for power and control. From their cold detachment to the dark fantasies that fuel their actions, the post explores the chilling traits and motivations behind these killers. With a focus on the haunting impact on victims and society, it offers a gripping, humanized look into the forces that drive someone to commit the unthinkable.

Read More »
Health
Mureithi Melvin

HEALTH REVIEW.

By Mureithi Melvin

Worth Noting:

Counseling, especially in today’s context, requires constant professional development and emotional investment. The mental and emotional toll it takes on practitioners is immense, yet they are often expected to provide their services without guaranteed financial support. This leaves them vulnerable to exploitation, which can further undermine the quality of services offered to those in need.
There is a pressing need for counselors to be enrolled in permanent and pensionable roles. A system that provides long-term employment opportunities would not only safeguard the well-being of counselors but also enhance the quality of care they provide. A permanent position allows for job security, benefits such as healthcare, and the peace of mind to focus on helping others without the constant fear of financial instability.
Pro bono services, while a noble undertaking, have long been the norm in the counseling profession. Many counselors, particularly those at the grassroots level, offer their expertise for free, driven by a passion to help individuals navigate life’s challenges. However, the practice of offering such services without financial compensation has serious implications, not only for the well-being of the counselors but also for the broader system of governance.

The Strain of Unpaid Work

While pro bono counseling offers critical support to marginalized and underserved communities, it places a significant strain on counselors who, more often than not, are working without the financial stability that paid employment offers. These professionals are highly trained and possess extensive qualifications, including a Bachelor of Arts in Counseling Psychology, but many still struggle to make a living through their work. The reality is that without financial compensation, counselors are often left to work in challenging conditions with little to no support, leading to burnout and high turnover rates within the field.

Counseling, especially in today’s context, requires constant professional development and emotional investment. The mental and emotional toll it takes on practitioners is immense, yet they are often expected to provide their services without guaranteed financial support. This leaves them vulnerable to exploitation, which can further undermine the quality of services offered to those in need.

The Call for Permanent and Pensionable Positions

There is a pressing need for counselors to be enrolled in permanent and pensionable roles. A system that provides long-term employment opportunities would not only safeguard the well-being of counselors but also enhance the quality of care they provide. A permanent position allows for job security, benefits such as healthcare, and the peace of mind to focus on helping others without the constant fear of financial instability.

Furthermore, pensionable employment would allow counselors to plan for their futures, as it ensures that they will be supported in their later years. The lack of such provisions often means that, after years of service, counselors are left without a safety net, making it difficult for them to retire with dignity. This is especially concerning when considering the emotional labor involved in the counseling profession.

Impact on Governance

The systemic integration of counselors into permanent and pensionable positions would have a profound impact on governance. By recognizing counselors as essential members of the workforce and providing them with stable employment, we are investing in the long-term mental and emotional health of our society. The counseling profession plays a critical role in addressing mental health issues, preventing crime, and fostering social cohesion. By ensuring that counselors are properly compensated, we acknowledge their value and prioritize mental health at the governance level.

In turn, when counselors are financially secure, they can better contribute to policy development and advocacy. Their experience and expertise become invaluable in shaping mental health frameworks, supporting vulnerable populations, and developing educational programs to prevent mental health crises. This strengthens the overall governance structure, as the well-being of citizens directly affects the stability and progress of any nation.

Conclusion

The time has come to move beyond the pro bono model for counselors and recognize their vital contribution to society. By providing permanent, pensionable employment, we are not only investing in the future of counselors but also in the future of our communities and governance structures. As a society, we must advocate for the fair treatment of mental health professionals, ensuring they are adequately compensated for their work. By doing so, we enhance not only their professional satisfaction but also the overall quality of life for the individuals and communities they serve. It’s time to give counselors the support they deserve, creating a sustainable and impactful mental health infrastructure for generations to come.

Prepared by, Mureithi Melvin, BA (Couns. Psych.) Ongoing- KCA, Dip. (Couns. Psych.), Hons. Doc. (Trg.) – Ulumudin Markaz, Assoc. Psych. (KCPA), Mental Health Advocate, ISSUP Member.

Read More »
Health
ketaki baravkar

MAOA and CDH13: An Overview of Gene Anatomy, Structural Variations, and Behavioral Implications

The MAOA and CDH13 genes play crucial roles in neurobiology, influencing neurotransmitter metabolism and neuronal connectivity. Variants in these genes are linked to aggression, impulsivity, and psychiatric disorders. While research supports these associations, gaps remain in understanding gene-environment interactions, ethnic variations, and precise molecular mechanisms affecting behavior and mental health.

Read More »
Health
Niharika Punia

HOW CHILDHOOD TRAUMA INFLUENCES SPIRITUAL AWAKENING, ETHICAL REASONING, AND HEALING

Childhood trauma profoundly shapes spiritual beliefs, moral reasoning, and healing paths. Many survivors experience spiritual awakening, explore mysticism, or shift their ethical perspectives to find meaning. Understanding these transformations helps in developing holistic trauma recovery approaches, fostering post-traumatic growth, resilience, and deeper existential awareness in survivors’ healing journeys.

Read More »
Health
khushi Jain

The Impact of Sleep Deprivation on Cognitive Function and Daily Life

Khushi Jain , Bhumi Sharma  ‘Sleep Deprivation’ or Insufficient sleep to meet an individual’s physiological and psychological needs is getting more common day by day due to lifestyle changes, work schedules and even health-related concerns. Many people, motivated by the need to be the best , prioritize their work, social meetings and activities, or even their screen time over sleep, leading to a delay in melatonin production which in turn disrupts their biological clock and sleep-wake cycles. Without proper sleep, individuals can show a significant decline in various areas of cognitive abilities like alertness, vigilance, attention and concentration. Evidence also suggests that sleep deprivation can also affect higher order cognitive processes, such as problem solving and decision making, as many of these higher order capabilities are believed to be moderated by the prefrontal cortex, which is supposed to be affected by prolonged sleep disturbance.   The Link Between Repetitive Negative Thinking and Sleep Disturbances Consistent with prominent theories of psychopathology, research has reliably shown repetitive negative thinking (RNT) to be a central characteristic of many psychiatric conditions (Beck & Clark, 1988; Borkovec, Alcaine, & Behar, 2004; Rachman, 1997)(Stewart et al., 2018). RNT can manifest in many ways including worry, rumination, and obsessing, but has the shared feature that it is exhibited as frequent negative thoughts that are difficult to control (Ehring & Watkins, 2008). In addition to being characterized by elevated RNT, many psychiatric disorders are also characterized by disruptions in the duration and timing of sleep (Apa, 2013; Boivin, 2000; Harvey, 2008, 2011; Wulff, Gatti, Wettstein, & Foster, 2010)(Stewart et al., 2018). Harvey, Murray, Chandler, and Soehner (2011) argue that sleep disturbance should be viewed as a transdiagnostic process, as it is a feature of most psychiatric conditions. For example, sleep disruptions are reported by up to 90% of those experiencing an acute depressive episode (Wulff et al., 2010) (Stewart et al., 2018).  A number of studies document a relationship between Repetitive Negative Thinking (RNT) and reductions in sleep duration or quality (Fairholme et al. 2013; Guastella and Moulds 2007; Harvey 2002; Thomsen et al. 2003; Zoccola et al. 2009) (Nota & Coles, 2014). For example, sleep deprivation has been linked to increased rumination and decreased mood (Baglioni et al. 2010; Pilcher and Huffcutt 1996; Walker 2009) (Nota & Coles, 2014). However, there is still more to be learned about the relation between RNT and sleep duration. Experimental studies that induce rumination or worry prior to sleep have been shown to reduce sleep quality (Gross and Borkovec 1982; Vandekerckhove et al. 2012) and naturally occurring levels of RNT have been shown to prospectively predict sleep quality (Takano et al. 2012) (Nota & Coles, 2014).  The Link Between Social Isolation, Loneliness, and Sleep Disturbances A large number of older people encounter both objective and subjective types of social isolation and sleep disorders. Social isolation increases a person’s risk of a wide range of adverse health outcomes and premature death. Social isolation can cause poor sleep quality that has been proposed as one of the possible mechanisms by which social isolation affects people’s health and quality of life. (Azizi-Zeinalhajlou et al., 2022)  Another similar factor is loneliness, which can be defined as the feeling of being separate from others, and has been identified as one key aspect of social factors that influence health (Cacioppo and Hawkley (2003) proposed that sleep disturbance is a mechanism through which loneliness influences health, citing two studies led by (Cacioppo (2002a, 2002b) in which lonely persons reported lower sleep quality and showed lower sleep efficiency and higher levels of wake time after sleep onset than non-lonely persons. Therefore, it is essential to comprehend these issues and address them through various treatment plans. The Impact of Sleep Deprivation on Psychological Functioning Sleep deprivation or insufficient sleep is very intricately connected to negative thinking. As we know, lack of rest and proper sleep makes the brain more volatile and more susceptible to emotional reactions and distressing thoughts and feelings. When the brain does not get enough sleep, the prefrontal cortex, which oversees rational thinking, weakens, whereas the amygdala, responsible for processing emotions, becomes increasingly reactive. These imbalances cause a lot of irregularities in an individual, such as frequent mood swings, increasing anxiety as well as ruminating or over-fixating on a problem. Chronic sleep deprivation plays a role in escalating mild symptoms of disorders like anxiety and depression but it also majorly increases the risk of developing serious mental health conditions and disorders. Prolonged sleep deprivation disrupts the brain’s neural pathways, especially those involved in emotional regulation and stress response, which reduces the brain’s ability to recover from emotional strain and cope with daily stressors. Over time, this disruption can have lasting psychological effects, as the brain’s resilience against stress weakens, making it more susceptible to mood disturbances and mental health disorders (Jansen & Narayan, 2024).  There is sufficient evidence to show the relationship between sleep disturbance and negative thinking. Sleep is an important factor to consider in developmental psychopathology (Meltzer, 2016). In adults, higher levels of RNT are associated with longer sleep onset latency and poorer sleep quality (Guastella & Moulds, 2007; Nota & Coles, 2015; Zoccola, Dickerson, & Lam, 2009). Further, an initial study in adults that incorporated both sleep duration and sleep timing components in one study found that sleep timing uniquely impacted RNT. Specifically, delayed sleep timing was associated with higher levels of RNT (Nota & Coles, 2015). This can have a serious effect on a person’s mental, emotional and physical well-being. Studies have shown that prolonged insufficient sleep can reduce the size of the hippocampus, which deals with memory and emotional regulation, making one more susceptible towards mental health conditions like anxiety and depression. Due to sleep deprivation, the brain loses its ability to regulate emotions and process information which leads to heightened stress responses and difficulty in concentrating. It can also tamper with the production of neurotransmitters like serotonin and dopamine, which plays an important role in stabilizing mood. This can cause

Read More »
Health
Ayush Burnwal

THE IMPACT OF COVID-19 ON HEALTHCARE INEQUITIES:- Assessing the long-term Economic consequences on Vulnerable Population

 HEALTHCARE ECONOMICS  THE IMPACT OF COVID-19 ON HEALTHCARE INEQUITIES:- Assessing the long-term Economic consequences on Vulnerable Population   By:- Sheetal  Ayush Burnwal Zaheen Qureshi Sanjula D Pankhudi Jha             INTRODUCTION The first whispers about an obscure virus were heard in Wuhan, China. A few months later, it began to spread, accompanying the number of cases contaminated rising swiftly and comprehensively in domains of the world for fear that on March 11, 2020, the WHO regularly announced the new affliction as a worldwide universal. The disease has a development ending from two to fourteen days but generally remains asymptomatic. If indicative, the universal signs and symptoms noticed include turmoil, dry cough, shortness of whiff, proneness, neck sensitivity, restlessness, and in harsh cases leads to severe respiratory distress syndrome and pneumonia that in decay can finish in multiple means of loss and certainly death. The harsh performance of affliction was majorly seen in toddlers and aging old people. Many measures were taken to stop the affliction i.e. seclusion, quarantine of distrust, tight infection administration conduct, contact security measures, and social passing.  In reference to this healthcare inequities may be delimited as differences in healthcare rank or the disposal of well-being resources between various populace groups, arising from public environments at which point people are innate, evolve, live, work, and age. Health inequities are prejudiced and could be weakened for one right join of government tactics. A big culture, variations in possessions across domains, and a feeble community health system in India formal a challenge in conditions of momentary and preparedness to handle a quickening caseload.16 In conditions of available capital, from the 3.6% GDP expense in healthcare, only 1.5% is apiece Government, and households carry more than 2%, that is to say, 65% of payment is out of pocket.12 The system working, when COVID hit, was accordingly underprepared to deal with this crisis. The risk of harsh complexities from COVID-19 is higher for certain unsafe people, particularly the ones who are retired, frail, or have diversified never-ending environments. The other susceptible group is made apiece stranded, weak, regular traders as the ever-growing strength cost keeps aggressive those just above the poverty line back into want. Vulnerable societies were individual big groups in India, labeled all along COVID. OBJECTIVE  To examine healthcare inequities from a multidimensional lens of economics, in the aftermath of COVID-19.      HEALTHCARE INEQUITIES India however confronts many difficulties in providing equitable healthcare to all due to its large population. Healthcare inequities are influenced by a number of factors such as socioeconomic status, regional differences, inadequate healthcare facilities, gender stereotypes, etc. These inequities produce systematic disadvantages and cause disparities among different sections of the population.   The rural population often prefers public health because it provides them with the most accessible and affordable healthcare option, as they typically lack the financial means to access private healthcare services, which are often more expensive and may not be readily available in their communities. It is, therefore, the public health system that serves the majority of India’s vulnerable rural population. Nearly 75 percent of health-related infrastructure, medical workforce, and other health resources are concentrated in urban areas, where only 27 percent of the population resides. This leaves the poorest segments of the population in rural areas facing numerous access barriers.    Providing well-equipped public healthcare becomes quintessential in reducing inequities between the rural and the urban. It is therefore important to have a strong and effective public healthcare system as the rural population’s access to basic health services is mainly through primary healthcare centers which is widely regarded as the most inclusive, equitable, and cost-effective way to achieve universal health coverage. PHCs in India are understaffed as more than 37% of the health assistant positions, 34% of laboratory staff and 21% of nurse positions are vacant. There is widespread absenteeism among healthcare workers in PHCs. Due to poor management and ill-equipped services provided by PHCs, the rural population is forced to seek services from the private sector, causing more financial complications and widening the rural-urban gap.   One of the main challenges is that health spending in India is mostly out-of-pocket. OOP health expenditure imposes an extreme financial burden on households because the fees and cost of treatment are very high in private facilities and unaffordable for people earning low incomes. OOP expenditure on health is one of the biggest reasons for people falling into poverty in India.   Nearly 70% of hospitals and 40% of hospital beds are private. Health insurance is largely private, and the urban poor cannot afford private care. The Indian healthcare budget is inadequate; the total healthcare expenditure was at only 1.3% of gross domestic product in 2021, which is the lowest in the BRICS group. There is a disparity in the availability of infrastructure and resources between rural and urban areas in India. Evidence points out that among all health workers, 67% were serving in urban areas where 33% of the population is based; and 33% were serving in rural areas where 67% of the population resides. India has approximately 860 beds/million population as compared to WHO’s estimate of the world average, which is 3,960 beds/million population, proving that our healthcare infrastructure is seriously lacking.    Gender stereotypes and inequalities can also impact access to healthcare, particularly for women. Cultural norms may limit women’s autonomy in making health decisions, leading to delays in seeking care or requiring approval from male family members. Additionally, gender-based discrimination and violence can further hinder women’s access to medical services. Women and elderly patients often rely on family support to reach healthcare facilities and may need permission before spending money on treatment, taking tests, or attending follow-up appointments.   India is a major hub for private health tourism. Private hospitals in India are seeing an influx of patients. India ranks among the top 20 countries in terms of private expenditure on health in percent GDP terms – around 4.5-5 percent of GDP. The extra revenue

Read More »